Prolotherapie (“proliferation therapy”) is een regeneratieve techniek waarbij wij een hypertone dextrose-oplossing injecteren in pijnlijke banden, pezen of gewrichten. Het stimuleert het lichaam om eigen herstelweefsel aan te maken.
Op deze pagina10
Hoe werkt het?
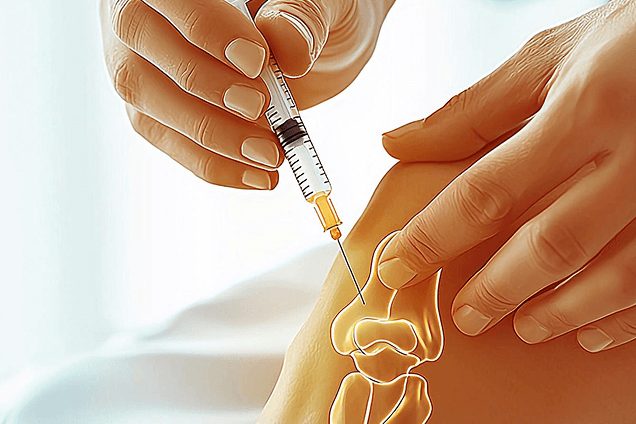
Een gefilterde dextrose-oplossing (meestal 15-25%) wordt gemengd met een lokaal anestheticum (lidocaïne) en met dunne naalden in specifieke aanhechtingspunten van pezen en ligamenten geïnjecteerd. De arts werkt op basis van anatomische landmarks of onder echografische begeleiding.
Per sessie worden vaak meerdere injectiepunten behandeld. De geïnjecteerde dextrose veroorzaakt een gecontroleerde, milde ontstekingsreactie waardoor het lichaam fibroblasten stuurt om collageen te vormen — daadwerkelijk herstel van het weefsel.
Wat kunt u verwachten?
Een sessie duurt 20-40 minuten. De injecties zijn kort prikkend; daarna ontstaat 24-72 uur een doffe, drukkende pijn op de behandelplek — dat is de gewenste ontstekingsreactie en hoort bij het herstelproces.
Belangrijk: pijnstillers zoals ibuprofen worden afgeraden omdat ze het herstelproces remmen. Paracetamol mag wel. Eerste 3-5 dagen rustig aan met sport; daarna geleidelijk opbouwen.
Wetenschappelijke onderbouwing
Gematigd bewijs bij knieartrose, laterale epicondylitis (tenniselleboog) en achillespees-tendinopathie. Het werkingsmechanisme wordt nog onderzocht. De American College of Rheumatology adviseerde in 2019 terughoudendheid bij knieartrose vanwege wisselende studie-kwaliteit.
Waar uw pijn vandaan komt
Ligamenten zijn de banden die uw gewrichten bij elkaar houden. Pezen verbinden de spieren aan het bot. Samen houden ze een gewricht op zijn plek en in beweging. Zijn ze beschadigd of opgerekt, dan doet dat pijn.
En dat gebeurt vaak. Veruit de meeste orthopedische pijnklachten komen voort uit beschadigde of instabiele ligamenten, kraakbeen, pezen en spieraanhechtingen. Door een ongeluk, een sportletsel of jarenlange overbelasting kunnen die scheuren, oprekken en minder elastisch worden. Denk aan een oud elastiek: dat kan minder hebben en knapt eerder.
Een compleet gescheurd ligament moet een chirurg repareren. Maar de meeste klachten komen niet van zo’n complete scheur. Ze komen van weefsel dat verzwakt, overrekt, overbelast en instabiel is geworden.
Daar blijft het niet bij. Als ligamenten en pezen een gewricht niet meer kunnen stabiliseren, ontstaat gewrichtsinstabiliteit. Dat kan leiden tot pijn, dysfunctie, artrose, kraakbeenschade en nog veel meer chronische problemen.
Waarom dat weefsel zelf niet geneest
Ligamenten hebben weinig bloedvoorziening. Daardoor genezen ze van nature slecht. Raakt een ligament beschadigd of opgerekt, dan herstelt het vaak maar gedeeltelijk. Vergelijk het met een spierletsel of een wondje op uw huid: die zitten vol bloedvaten en genezen meestal snel.
Misschien herkent u dat. Een oud letsel dat nooit helemaal goed kwam. Of pijn zonder duidelijk aanwijsbare oorzaak, waarvoor u al rust, fysiotherapie of chiropractie probeerde. Prolotherapie is in Nederland weinig bekend, maar het is een effectieve behandeling, juist omdat het niet de pijn aanpakt maar de verzwakte structuur eronder.
Wat de prik in uw lichaam op gang brengt
Bij letsel van een pees, ligament, gewricht of spieraanhechting reageert uw lichaam met een ontstekingsreactie. Dat klinkt verkeerd, maar het is de natuurlijke manier waarop uw lichaam schade repareert. Verwar het niet met een bacteriële infectie — daar zit een bacterie achter, hier niet.
Precies die reactie roepen wij op. De hoge concentratie glucose veroorzaakt een osmotische shockreactie op de plek waar we prikken. Met de naald maken we bovendien kleine, gecontroleerde wondjes. Uw lichaam behandelt het oude, slecht genezen letsel daardoor weer als een vers letsel. De bloedtoevoer verbetert en er komen meer reparatiecellen en groeifactoren naar het gebied. Dat u daarna een paar dagen napijn, stijfheid en beursheid voelt, hoort daarbij.
Hier komt ook het advies over pijnstillers vandaan. Ontstekingsremmers (NSAID’s) zoals diclofenac, ibuprofen of naproxen stillen wel de pijn, maar ze remmen de genezingsreactie waar we het juist van moeten hebben. Ook na een acuut spier-, pees- of ligamentletsel zijn ze om die reden geen goed idee.
Wat er daarna gebeurt, is de kern van de behandeling. Uw lichaam maakt nieuw, gezond bindweefsel aan: collageen. Ligamenten en pezen prolifereren — ze worden dikker en sterker en kunnen hun taak weer vervullen. Rug, nek, bekken en gewrichten worden stabieler. Overbelaste spieren en spierknopen kunnen eindelijk ontspannen. En de pijn vermindert sterk.
Glucose is wereldwijd het oudste en meest gebruikte middel hiervoor, vanwege de veiligheid en de effectiviteit. Er zijn ook andere stoffen die zo’n genezingsreactie kunnen uitlokken of stimuleren. Naar ozongas en Platelet Rich Plasma is de laatste jaren bijvoorbeeld veel onderzoek gedaan.
Aantal behandelingen
Eerst beoordelen we of u in aanmerking komt. Daarna hangt het aantal behandelingen af van wat u heeft, want prolotherapie wordt bij zeer uiteenlopende aandoeningen toegepast. Bij eenvoudige letsels zijn 1 tot 3 behandelingen genoeg. Bij uitgebreide en ernstige gevallen kunnen het er meer dan 10 zijn. Bij de gemiddelde patiënt met rugklachten beginnen we met een serie van 6 wekelijkse behandelingen. Prolotherapie van de wervelkolom doen we altijd samen met chiropractie en manuele therapie — dat geeft het beste resultaat.
Veruit de meeste patiënten hebben goed resultaat, zelfs bij klachten die al jaren bestaan. Zoals bij elke medische behandeling verschillen de resultaten; uw algehele gezondheid en uw leefstijl spelen mee. De behandeling zelf is veilig: we prikken alleen, we snijden niet, en er zijn nagenoeg geen bijwerkingen.
Klachten die we met prolotherapie behandelen
- Rugpijn, facetsyndroom, spit, acute rugklachten, chronische rugklachten
 Nekpijn en whiplashMeer over Nekpijn & whiplash
 Bekkenpijn, SI-syndroom en bekkeninstabiliteitMeer over Bekkeninstabiliteit
- Schouderinstabiliteit en schouderpijn
- Peesontstekingen en chronische peesproblemen
- Tenniselleboog en golferselleboog
 Heuppijn en heupartroseMeer over Heupartrose
 Kniepijn en knieartroseMeer over Knieartrose
- Enkelklachten
Deze lijst is niet volledig. Op onze pagina’s en blogposts leest u meer over de aandoeningen en klachten die wij behandelen.
Zo verloopt een sessie
Elk traject is maatwerk, maar zo ziet een typisch verloop eruit — van eerste intake tot pijnvrij en onderhoud. U weet steeds precies waar u aan toe bent.
Markeren & voorbereiding
Arts identificeert de exact behandelpunten op pezen en ligamenten. Huid desinfecteren. Dextrose-oplossing klaarmaken.
Series injecties
Meerdere injecties (vaak 5-15) op specifieke aanhechtingen. Kort prikkend gevoel; lokaal anestheticum kan ongemak verlichten.
Eerste reactie
Kort rusten. Arts checkt of u zich goed voelt. Geen ibuprofen — wel paracetamol mag voor ongemak.
Herstel-reactie
Doffe pijn op behandelplek 1-3 dagen — dit is GEWENST, het is de ontstekingsreactie die het herstel start. Sporten 3-5 dagen rustig aan.
Veelgestelde vragen
Is het hetzelfde als een corticosteroïd-injectie?
Nee. Corticosteroïden remmen ontsteking; prolotherapie wékt juist een herstelreactie op zodat het weefsel sterker wordt.
Mag ik sporten erna?
Eerste 3-5 dagen rustig aan; daarna geleidelijk opbouwen.
Wordt het vergoed?
Meestal niet via basisverzekering; soms via aanvullende pakketten. Check via onze vergoedingen-tool.
Is het pijnlijk?
De prik valt mee; de naprikkel-pijn duurt 1-3 dagen en is onderdeel van het werkingsmechanisme.
Hoe lang houdt het effect aan?
Bij goede respons jaren tot blijvend, omdat het weefsel daadwerkelijk is versterkt.
Niet geschikt bij lokale infectie, bloedstollingsstoornissen, gebruik van antistolling (relatief), allergie voor dextrose of lidocaïne, acute septische artritis of ongecontroleerde diabetes. Standaard 3-6 sessies met 2-6 weken interval.
Wetenschappelijke referenties (48)
Toon alle bronnenVerberg de bronnen
- Hsu C, Vu K, Borg-Stein J. Prolotherapy: A Narrative Review of Mechanisms, Techniques, and Protocols, and Evidence for Common Musculoskeletal Conditions. Phys Med Rehabil Clin N Am. 2023 Feb;34(1):165-180. doi: 10.1016/j.pmr.2022.08.011. Epub 2022 Oct 18. PMID: 36410881.
- Cortez VS, Moraes WA, Taba JV, Condi A, Suzuki MO, Nascimento FSD, Pipek LZ, Mattos VC, Torsani MB, Meyer A, Hsing WT, Iuamoto LR. Comparing dextrose prolotherapy with other substances in knee osteoarthritis pain relief: A systematic review. Clinics (Sao Paulo). 2022 May 17;77:100037. doi: 10.1016/j.clinsp.2022.100037. Epub ahead of print. PMID: 35594623; PMCID: PMC9123214.
- Haggag MA, Al-Belasy FA, Said Ahmed WM. Dextrose prolotherapy for pain and dysfunction of the TMJ reducible disc displacement: A randomized, double-blind clinical study. J Craniomaxillofac Surg. 2022 Mar 8:S1010-5182(22)00025-7. doi: 10.1016/j.jcms.2022.02.009. Epub ahead of print. PMID: 35501215.
- Eroglu A, Yargic MP. Effectiveness of Ultrasound-Guided Corticosteroid Injections, Prolotherapy, and Exercise Therapy on Partial-Thickness Supraspinatus Tears. J Sport Rehabil. 2022 Apr 21:1-7. doi: 10.1123/jsr.2021-0254. Epub ahead of print. PMID: 35453118.
- Hsieh RL, Lee WC. Effects of Intra-Articular Coinjections of Hyaluronic Acid and Hypertonic Dextrose on Knee Osteoarthritis: A Prospective, Randomized, Double-Blind Trial. Arch Phys Med Rehabil. 2022 Apr 16:S0003-9993(22)00344-6. doi: 10.1016/j.apmr.2022.04.001. Epub ahead of print. PMID: 35439521.
- Chutumstid T, Susantitapong P, Koonalinthip N. Effectiveness of Dextrose prolotherapy for the treatment of chronic Plantar Fasciitis: A Systematic Review and Meta-Analysis of Randomized Controlled Trials. PM R. 2022 Mar 25. doi: 10.1002/pmrj.12807. Epub ahead of print. PMID: 35338597.
- Chen YW, Lin YN, Chen HC, Liou TH, Liao CD, Huang SW. Effectiveness, Compliance, and Safety of Dextrose Prolotherapy for Knee Osteoarthritis: A Meta-Analysis and Metaregression of Randomized Controlled Trials. Clin Rehabil. 2022 Mar 8:2692155221086213. doi: 10.1177/02692155221086213. Epub ahead of print. PMID: 35257594.
- Zhu M, Rabago D, Chung VC, Reeves KD, Wong SY, Sit RW. Effects of Hypertonic Dextrose Injection (Prolotherapy) in Lateral Elbow Tendinosis: A Systematic Review and Meta-analysis. Arch Phys Med Rehabil. 2022 Feb 28:S0003-9993(22)00240-4. doi: 10.1016/j.apmr.2022.01.166. Epub ahead of print. PMID: 35240122.
- Won SJ, Kim DY, Kim JM. Effect of platelet-rich plasma injections for chronic nonspecific low back pain: A randomized controlled study. Medicine (Baltimore). 2022 Feb 25;101(8):e28935. doi: 10.1097/MD.0000000000028935. PMID: 35212300; PMCID: PMC8878905.
- Hauser RA, Matias D, Woznica D, Rawlings B, Woldin BA. Lumbar instability as an etiology of low back pain and its treatment by prolotherapy: A review. J Back Musculoskelet Rehabil. 2021 Dec 14. doi: 10.3233/BMR-210097. Epub ahead of print. PMID: 34957989.
- Sit RWS, Wu RWK, Rabago D, et al. Efficacy of Intra-Articular Hypertonic Dextrose (Prolotherapy) for Knee Osteoarthritis: A Randomized Controlled Trial. Ann Fam Med. 2020;18(3):235-242. doi:10.1370/afm.2520
- Sert AT, Sen EI, Esmaeilzadeh S, Ozcan E. The Effects of Dextrose Prolotherapy in Symptomatic Knee Osteoarthritis: A Randomized Controlled Study. J Altern Complement Med. 2020;26(5):409-417. doi:10.1089/acm.2019.0335
- Coombes BK, Bisset L, Vicenzino B. Efficacy and safety of corticosteroid injections and other injections for management of tendinopathy: a systematic review of randomised controlled trials. Lancet. 2010 Nov 20;376(9754):1751-67. doi: 10.1016/S0140-6736(10)61160-9. Epub 2010 Oct 21. Review. PubMed PMID: 20970844.
- Klein RG, Eek BC, DeLong WB, Mooney V. A randomized double-blind trial of dextrose-glycerine-phenol injections for chronic, low back pain. J Spinal Disord. 1993 Feb;6(1):23-33. PubMed PMID: 8439713.
- Arias-Vázquez PI, Tovilla-Zárate CA, Legorreta-Ramírez BG, Burad Fonz W, Magaña-Ricardez D, González-Castro TB, Juárez-Rojop IE, López-Narváez ML. Prolotherapy for knee osteoarthritis using hypertonic dextrose vs other interventional treatments: systematic review of clinical trials. Adv Rheumatol. 2019 Aug 19;59(1):39. doi: 10.1186/s42358-019-0083-7. Review. PubMed PMID: 31426856.
- Catapano M, Zhang K, Mittal N, Sangha H, Onishi K, de Sa D. Effectiveness of Dextrose Prolotherapy for Rotator Cuff Tendinopathy: A Systematic Review. PM R. 2019 Oct 22. doi: 10.1002/pmrj.12268. [Epub ahead of print] PubMed PMID: 31642203.
- Louw WF, Reeves KD, Lam SKH, Cheng AL, Rabago D. Treatment of Temporomandibular Dysfunction With Hypertonic Dextrose Injection (Prolotherapy): A Randomized Controlled Trial With Long-term Partial Crossover. Mayo Clin Proc. 2019 Mar 13. pii: S0025-6196(18)30678-5. doi: 10.1016/j.mayocp.2018.07.023. [Epub ahead of print] PubMed PMID: 30878157.
- Lin CL, Huang CC, Huang SW. Effects of hypertonic dextrose injection on chronic supraspinatus tendinopathy of the shoulder: randomized placebo-controlled trial. Eur J Phys Rehabil Med. 2018 Dec 13. doi: 10.23736/S1973-9087.18.05379-0. [Epub ahead of print] PubMed PMID: 30543266.
- HACKETT GS, HENDERSON DG. Joint stabilization; an experimental, histologicstudy with comments on the clinical application in ligament proliferation. Am JSurg. 1955 May;89(5):968-73. PubMed PMID: 14361880.
- HACKETT GS. Shearing injury to the sacroiliac joint. J Int Coll Surg. 1954Dec;22(6 Pt 1):631-42. PubMed PMID: 13221832.
- Jensen KT, Rabago DP, Best TM, Patterson JJ, Vanderby R Jr. Response of kneeligaments to prolotherapy in a rat injury model. Am J Sports Med. 2008Jul;36(7):1347-57. doi: 10.1177/0363546508314431. Epub 2008 Feb 29. PubMed PMID:18310313; PubMed Central PMCID: PMC3164307.
- Maynard JA, Pedrini VA, Pedrini-Mille A, Romanus B, Ohlerking F. Morphologicaland biochemical effects of sodium morrhuate on tendons. J Orthop Res.1985;3(2):236-48. PubMed PMID: 3998899.
- Liu YK, Tipton CM, Matthes RD, Bedford TG, Maynard JA, Walmer HC. An in situstudy of the influence of a sclerosing solution in rabbit medial collateralligaments and its junction strength. Connect Tissue Res. 1983;11(2-3):95-102.PubMed PMID: 6224646.
- Ongley MJ, Klein RG, Dorman TA, Eek BC, Hubert LJ. A new approach to thetreatment of chronic low back pain. Lancet. 1987 Jul 18;2(8551):143-6. PubMedPMID: 2439856.
- Cusi M, Saunders J, Hungerford B, Wisbey-Roth T, Lucas P, Wilson S. The use ofprolotherapy in the sacroiliac joint. Br J Sports Med. 2010 Feb;44(2):100-4. doi:10.1136/bjsm.2007.042044. Epub 2008 Apr 9. PubMed PMID: 18400878.
- Klein RG, Eek BC, DeLong WB, Mooney V. A randomized double-blind trial ofdextrose-glycerine-phenol injections for chronic, low back pain. J Spinal Disord.1993 Feb;6(1):23-33. PubMed PMID: 8439713.
- Kim WM, Lee HG, Jeong CW, Kim CM, Yoon MH. A randomized controlled trial ofintra-articular prolotherapy versus steroid injection for sacroiliac joint pain.J Altern Complement Med. 2010 Dec;16(12):1285-90. doi: 10.1089/acm.2010.0031.PubMed PMID: 21138388.
- Hooper RA, Frizzell JB, Faris P. Case series on chronic whiplash related neckpain treated with intraarticular zygapophysial joint regeneration injectiontherapy. Pain Physician. 2007 Mar;10(2):313-8. PubMed PMID: 17387354.
- Rabago D, Kijowski R, Woods M, Patterson JJ, Mundt M, Zgierska A, Grettie J,Lyftogt J, Fortney L. Association between disease-specific quality of life andmagnetic resonance imaging outcomes in a clinical trial of prolotherapy for kneeosteoarthritis. Arch Phys Med Rehabil. 2013 Nov;94(11):2075-82. doi:10.1016/j.apmr.2013.06.025. Epub 2013 Jul 10. PubMed PMID: 23850615; PubMedCentral PMCID: PMC3812343.
- Reeves KD, Hassanein KM. Long-term effects of dextrose prolotherapy foranterior cruciate ligament laxity. Altern Ther Health Med. 2003May-Jun;9(3):58-62. PubMed PMID: 12776476.
- Hung CY, Hsiao MY, Chang KV, Han DS, Wang TG. Comparative effectiveness ofdextrose prolotherapy versus control injections and exercise in the management ofosteoarthritis pain: a systematic review and meta-analysis. J Pain Res. 2016 Oct18;9:847-857. PubMed PMID: 27799816; PubMed Central PMCID: PMC5079700.
- Bertrand H, Reeves KD, Bennett CJ, Bicknell S, Cheng AL. Dextrose ProlotherapyVersus Control Injections in Painful Rotator Cuff Tendinopathy. Arch Phys MedRehabil. 2016 Jan;97(1):17-25. doi: 10.1016/j.apmr.2015.08.412. PubMed PMID:26301385.
- Lee DH, Kwack KS, Rah UW, Yoon SH. Prolotherapy for Refractory Rotator CuffDisease: Retrospective Case-Control Study of 1-Year Follow-Up. Arch Phys MedRehabil. 2015 Nov;96(11):2027-32. doi: 10.1016/j.apmr.2015.07.011. PubMed PMID:26254952.
- Rabago D, Mundt M, Zgierska A, Grettie J. Hypertonic dextrose injection(prolotherapy) for knee osteoarthritis: Long term outcomes. Complement Ther Med.2015 Jun;23(3):388-95. doi: 10.1016/j.ctim.2015.04.003. PubMed PMID: 26051574.
- Eslamian F, Amouzandeh B. Therapeutic effects of prolotherapy withintra-articular dextrose injection in patients with moderate knee osteoarthritis:a single-arm study with 6 months follow up. Ther Adv Musculoskelet Dis. 2015Apr;7(2):35-44. doi: 10.1177/1759720X14566618. PubMed PMID: 25829954; PubMedCentral PMCID: PMC4357593.
- Jahangiri A, Moghaddam FR, Najafi S. Hypertonic dextrose versus corticosteroidlocal injection for the treatment of osteoarthritis in the first carpometacarpaljoint: a double-blind randomized clinical trial. J Orthop Sci. 2014Sep;19(5):737-43. doi: 10.1007/s00776-014-0587-2. PubMed PMID: 25158896.
- Rabago D, Patterson JJ, Mundt M, Kijowski R, Grettie J, Segal NA, Zgierska A.Dextrose prolotherapy for knee osteoarthritis: a randomized controlled trial. AnnFam Med. 2013 May-Jun;11(3):229-37. doi: 10.1370/afm.1504. Erratum in: Ann FamMed. 2013 Sep-Oct;11(5):480. PubMed PMID: 23690322; PubMed Central PMCID:PMC3659139.
- Hashemi M, Jalili P, Mennati S, Koosha A, Rohanifar R, Madadi F, Razavi SS,Taheri F. The Effects of Prolotherapy With Hypertonic Dextrose Versus Prolozone(Intraarticular Ozone) in Patients With Knee Osteoarthritis. Anesth Pain Med.2015 Oct 17;5(5):e27585. doi: 10.5812/aapm.27585. PubMed PMID: 26587401; PubMedCentral PMCID: PMC4644302.
- Carayannopoulos A, Borg-Stein J, Sokolof J, Meleger A, Rosenberg D.Prolotherapy versus corticosteroid injections for the treatment of lateralepicondylosis: a randomized controlled trial. PM R. 2011 Aug;3(8):706-15. doi:10.1016/j.pmrj.2011.05.011. PubMed PMID: 21871414.
- Yelland MJ, Sweeting KR, Lyftogt JA, Ng SK, Scuffham PA, Evans KA.Prolotherapy injections and eccentric loading exercises for painful Achillestendinosis: a randomised trial. Br J Sports Med. 2011 Apr;45(5):421-8. doi:10.1136/bjsm.2009.057968. PubMed PMID: 19549615.
- Yelland MJ, Glasziou PP, Bogduk N, Schluter PJ, McKernon M. Prolotherapyinjections, saline injections, and exercises for chronic low-back pain: arandomized trial. Spine (Phila Pa 1976). 2004 Jan 1;29(1):9-16; discussion 16.PubMed PMID: 14699269.
- Morath O, Kubosch EJ, Taeymans J, Zwingmann J, Konstantinidis L, Südkamp NP, Hirschmüller A. The effect of sclerotherapy and prolotherapy on chronic painful Achilles tendinopathy-a systematic review including meta-analysis. Scand J Med Sci Sports. 2018 Jan;28(1):4-15. doi: 10.1111/sms.12898. Epub 2017 May 26. Review. PubMed PMID: 28449312.
- Seven MM, Ersen O, Akpancar S, Ozkan H, Turkkan S, Yıldız Y, Koca K.Effectiveness of prolotherapy in the treatment of chronic rotator cuff lesions.Orthop Traumatol Surg Res. 2017 May;103(3):427-433. doi:10.1016/j.otsr.2017.01.003. Epub 2017 Feb 16. PubMed PMID: 28215611.
- George J, Li SC, Jaafar Z, Hamid MSA. Comparative Effectiveness ofUltrasound-Guided Intratendinous Prolotherapy Injection with ConventionalTreatment to Treat Focal Supraspinatus Tendinosis. Scientifica (Cairo). 2018 Jul2;2018:4384159. doi: 10.1155/2018/4384159. eCollection 2018. PubMed PMID:30057849; PubMed Central PMCID: PMC6051036.
- Rahimzadeh P, Imani F, Faiz SHR, Entezary SR, Zamanabadi MN, Alebouyeh MR. Theeffects of injecting intra-articular platelet-rich plasma or prolotherapy on painscore and function in knee osteoarthritis. Clin Interv Aging. 2018 Jan4;13:73-79. doi: 10.2147/CIA.S147757. eCollection 2018. PubMed PMID: 29379278;PubMed Central PMCID: PMC5757490.
- Senturk E, Sahin E, Serter S. Prolotherapy: An effective therapy for Tietze syndrome. J Back Musculoskelet Rehabil. 2017 Sep 22;30(5):975-978. doi: 10.3233/BMR-159269. PubMed PMID: 28505950.
- Hauser RA, Lackner JB, Steilen-Matias D, Harris DK. A Systematic Review of Dextrose Prolotherapy for Chronic Musculoskeletal Pain. Clin Med Insights Arthritis Musculoskelet Disord. 2016 Jul 7;9:139-59. doi: 10.4137/CMAMD.S39160. eCollection 2016. Review. PubMed PMID: 27429562; PubMed Central PMCID: PMC4938120.